The Science
Measured medicine, not wishful wellness.
Longevity is not a supplement stack. It is the disciplined, decades-early management of the four systems that decide how long you stay healthy.
The premise
Lifespan is how long you live. Healthspan is how long you live well.
For most people the last decade of life is spent managing decline — medications, hospitals, shrinking independence. That gap between total years and healthy years is the real enemy, and it is measurable.
Longevity medicine exists to compress that decline into the smallest possible window: to keep the curve of your capability high and flat for as long as biology allows, then let it fall late and fast — instead of early and slowly.
Everything Genoryx does — 400+ parameters, quarterly retesting, physician-built protocols — serves that single graph.
Sample member · illustrative
- Chronological 45.0
- Biological 40.1
The four systems that end healthspan — and when they start.
Almost everything that shortens a healthy life runs through four biological systems. Each one begins its decline silently, decades before symptoms — which is exactly why we measure them early and repeatedly.
Cardiometabolic
The largest cause of death in India — and it starts 20-30 years before the event.
Atherosclerosis is a decades-long process. The markers that predict it — ApoB and Lp(a) — are rarely on a standard panel, yet they are measurable in your thirties, when there is still time to change the trajectory.
What we watch
ApoB, Lp(a), hs-CRP, HbA1c, fasting insulin, blood pressure, VO2 max
Oncologic
Most cancers are diagnosed late because nothing was looking early.
Survival is a function of stage at detection. A structured, physician-led screening calendar — not a one-off scan — is what shifts the odds.
What we watch
Age- and risk-guided screening calendar, inflammatory markers, family-history mapping
Neurodegenerative
Cognitive decline begins silently in midlife; by symptoms, decades have passed.
The brain ages through its blood vessels and its metabolism. The same markers that protect your heart protect your cognition — measured early, they are actionable.
What we watch
Metabolic and vascular risk markers, sleep quality, homocysteine, B12 / D status
Musculoskeletal
Falls and frailty end independence — muscle and bone decide how long you stay strong.
Muscle is the organ of longevity. Sarcopenia starts in the forties and accelerates — but it responds to training and protocols better than almost any other system.
What we watch
DEXA bone density and lean mass, grip strength, VO2 max, vitamin D, hormone panel
The silent decades.
Aging does not announce itself. Decade by decade, this is what is happening under “feeling fine” — and what each decade rewards.
What begins
Arterial plaque begins in susceptible lipid profiles. Insulin sensitivity starts drifting. Peak bone mass is behind you.
The move
The cheapest decade to act — baseline everything, correct early.
What begins
Muscle mass declines ~3-8% per decade from here. Hormones shift. Blood pressure creeps. First metabolic red flags surface.
The move
Trajectory-setting decade — training, metabolic and hormonal correction compound from here.
What begins
Cardiovascular events begin appearing in South Asian men. Bone density loss accelerates in women post-menopause.
The move
Screening intensity rises; prevention still outperforms treatment.
What begins
The gap between biological ages widens dramatically — two 65-year-olds can be a decade apart functionally.
The move
Everything invested earlier pays out here — strength, cognition, independence.
What you measure, you can change.
A number without interpretation is trivia. Interpreted by a physician, re-measured every quarter, it becomes the most powerful instrument in medicine: a trend.
The marker library — why each one matters.
A sample of what a 400+ parameter assessment actually buys you: not more numbers — fewer blind spots. Every marker below is measured, trended, and interpreted by a physician.
Cardiovascular
- ApoB
Counts the particles that actually cause plaque — better than LDL-C alone.
- Lp(a)
Genetic risk factor most Indians have never had measured. Once in a lifetime can change everything.
- hs-CRP
Vascular inflammation — the fire that accelerates plaque.
- Homocysteine
Elevated levels track with vascular and cognitive risk; often responds to B-vitamin status.
- Triglycerides / HDL-C
A fast, telling window into metabolic health.
Metabolic
- HbA1c
Three-month average blood sugar — the slow drift toward diabetes, visible early.
- Fasting insulin
Insulin resistance shows here years before glucose ever rises.
- Uric acid
Metabolic stress and dietary load marker; tracks with hypertension risk.
- Liver panel (ALT, GGT)
Fatty liver is the silent epidemic of Indian metros — visible in two numbers.
- eGFR / creatinine
Kidney reserve — the organ you never think about until it is late.
Hormonal
- Testosterone (total + free)
Energy, muscle, mood, drive — declining silently in urban Indian men.
- Estradiol / progesterone
The axis that governs female metabolic and bone health through perimenopause.
- Thyroid (TSH, free T3/T4)
The metabolic thermostat — subclinical dysfunction is common and missable.
- Cortisol
Chronic stress made measurable.
- DHEA-S / IGF-1
Recovery and anabolic reserve — context for everything above.
Inflammation & aging
- Epigenetic age (DNA methylation)
How old your body functionally is — the headline number, and it moves.
- hs-CRP / IL-6 family
"Inflammaging" — the slow burn that accelerates every system.
- Ferritin
Iron status and an inflammation signal in one.
- Omega-3 index
Membrane-level nutrition your diet claims but rarely delivers.
- Vitamin D / B12
Chronically low across India — cheap to fix, expensive to ignore.
Performance & body composition
- VO2 max
The single strongest fitness predictor of long-term mortality risk in the literature.
- DEXA lean mass & bone density
Gold-standard measurement of the muscle and bone you will live in at 80.
- Grip strength
A deceptively simple marker that tracks whole-body resilience.
- HRV & resting heart rate
Autonomic recovery — how well your system absorbs stress.
- CGM glucose patterns
What your meals actually do to you, hour by hour, not on average.
This is a sample. The full assessment spans 400+ parameters across 12 organ systems — every one reviewed with you, in person, by a physician.
Explore the diagnosticsThe instruments behind the numbers.
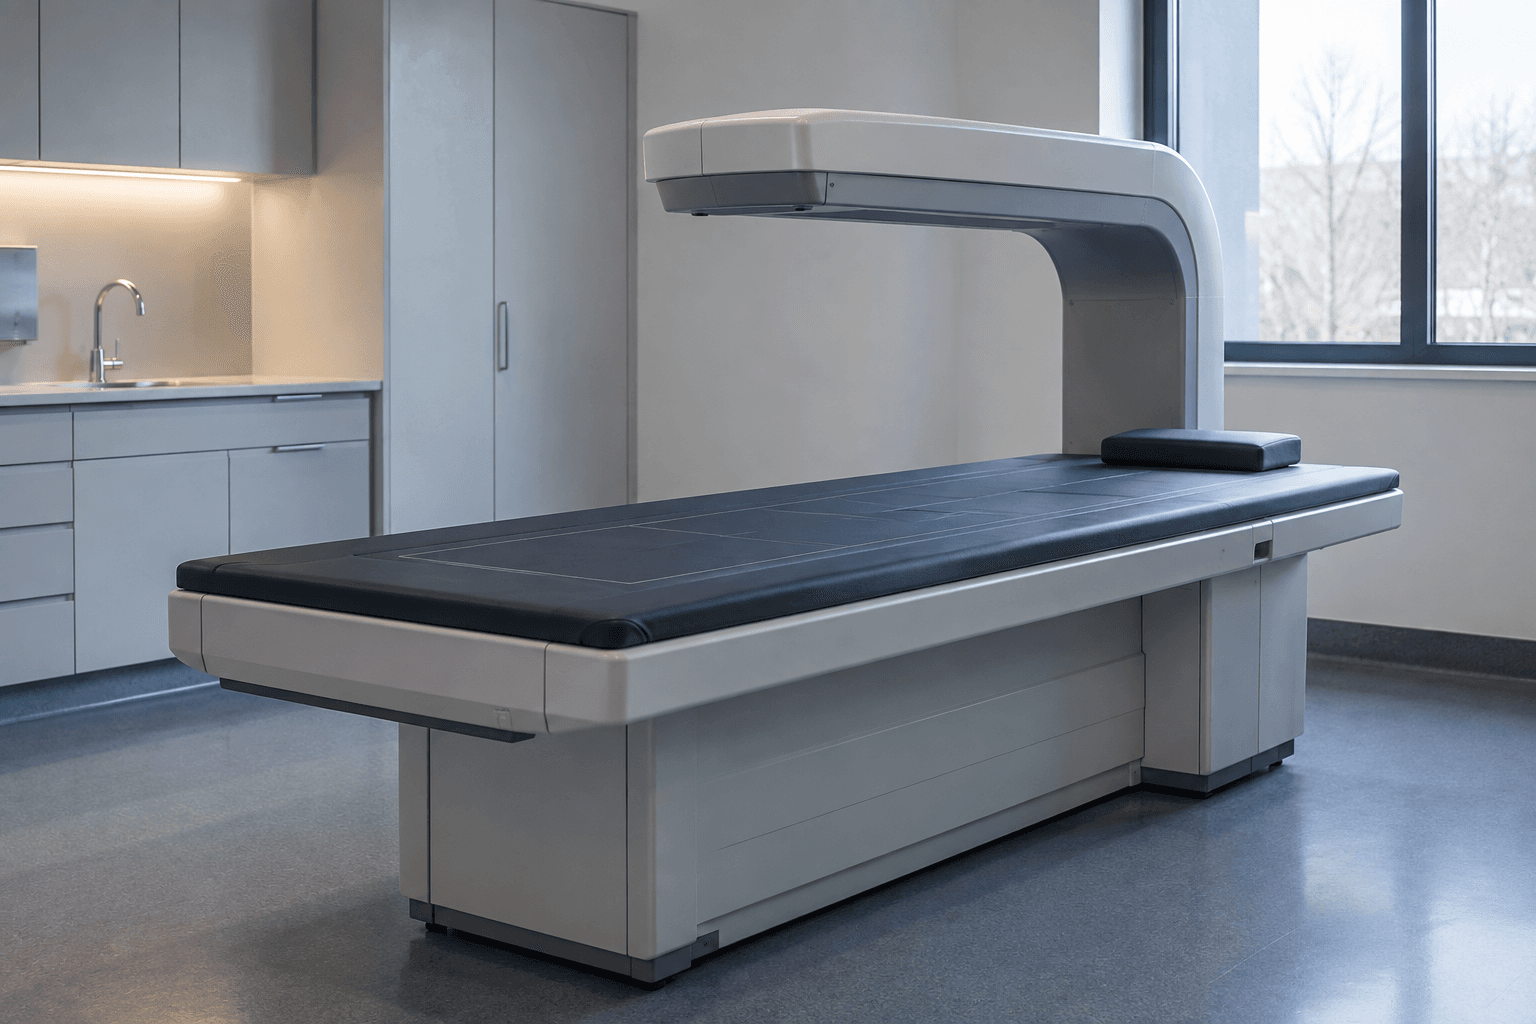
DEXA body composition
Gold-standard X-ray measurement of bone density, lean mass, and visceral fat — the fat that matters.

VO2 max testing
Cardiopulmonary exercise test measuring your aerobic engine — among the strongest known predictors of healthy lifespan.

Epigenetic age analysis
DNA methylation clocks estimate biological age and pace of aging — a research measure we track over time, not a treatment target.

Continuous glucose monitoring
Two to four weeks of real-world metabolic data — your actual responses to your actual life.
Normal is an average. Optimal is a target.
Standard lab ranges describe a population — including its unwell members. You can sit “within normal limits” on every line of a report while your risk quietly compounds for twenty years.
Genoryx panels are read against longevity-optimized ranges: the zones where long-term outcome data is strongest. Then we re-measure quarterly, because a single snapshot is a guess — a trend is knowledge.
Built for South Asian physiology.
Most reference data — and most wellness advice — is built on Western cohorts. That mismatch is not a detail. It is the difference between “you're fine” and “we should act now.”
earlier onset of cardiovascular disease in South Asian populations
thresholds at which insulin resistance and metabolic risk appear
lipid patterns — higher triglycerides, lower HDL at the same weight
Our physicians read every marker in the context of the population you actually belong to — one of the reasons physician review matters more than a printed report.
The evidence ladder.
Not every intervention deserves the same confidence — and a clinic that pretends otherwise is selling, not treating. This is how we hold ourselves honest.
Strength training, VO2 max development, sleep architecture, blood-pressure and lipid management, glycemic control
The core of every Genoryx protocol. Unglamorous, decisive, non-negotiable.
Hormone therapy for a diagnosed deficiency, targeted supplementation against measured deficiency, structured recovery (compression, heat/cold)
Deployed when your markers say so — never as a default, always re-measured.
NAD+ infusion, photobiomodulation (red light), HBOT for non-approved indications
Prescribed only where clinically indicated, with no anti-ageing claim. Plausible mechanisms, early evidence, and we tell you exactly what is and is not known.
We will say no. If the evidence does not support something — however fashionable — we will tell you plainly. Longevity medicine earns trust by what it refuses to sell.
Grounded in the literature.
The science we practice stands on decades of published research — these are some of the bodies of evidence our clinical reasoning draws on.
Epigenetic clocks
The DNA-methylation measures behind biological-age testing, from the first multi-tissue clock to pace-of-aging estimates.
- Horvath S. DNA methylation age of human tissues and cell types. Genome Biology, 2013.
- Levine ME, et al. An epigenetic biomarker of aging for lifespan and healthspan. Aging (Albany NY), 2018;10(4):573–591.
- Belsky DW, et al. DunedinPACE, a DNA methylation biomarker of the pace of aging. eLife, 2022.
Cardiorespiratory fitness and mortality
Large cohorts ranking VO2 max among the strongest predictors of how long, and how well, people live.
- Kodama S, et al. Cardiorespiratory fitness as a quantitative predictor of all-cause mortality and cardiovascular events. JAMA, 2009.
- Mandsager K, et al. Association of cardiorespiratory fitness with long-term mortality among adults undergoing exercise treadmill testing. JAMA Network Open, 2018.
ApoB and atherosclerotic risk
Why we count atherogenic particles rather than relying on LDL cholesterol alone.
- Sniderman AD, et al. Journal of the American Heart Association, 2022.
South Asian cardiometabolic risk
The evidence for earlier, steeper cardiometabolic risk in Indian and South Asian populations.
- Yusuf S, et al. INTERHEART study. The Lancet, 2004.
- Anjana RM, et al. ICMR-INDIAB Phase I. Indian Journal of Medical Research, 2017.
NAD+ biology
The mechanism work behind NAD+ infusion, which we still file under emerging evidence.
- Covarrubias AJ, et al. NAD+ metabolism and its roles in cellular processes during ageing. Nature Reviews Molecular Cell Biology, 2021.
Population cohorts
Framingham Heart Study and UK Biobank: decades of data linking biomarkers, lifestyle and long-term outcomes, the foundation of preventive cardiology.
Questions worth asking.
Why do you measure 400+ parameters when hospitals test 30?
A standard panel is built to detect existing disease. Ours is built to measure the trajectory toward it. Markers like ApoB, Lp(a), fasting insulin, and hs-CRP move decades before a diagnosis — and most are absent from routine checkups. More markers also means fewer blind spots across the 12 organ systems we map.
What does "longevity-optimized reference ranges" mean?
"Normal" lab ranges describe the average of a population that includes the unwell. Optimal ranges describe where the long-term risk data is lowest. Sitting at the edge of normal can still mean decades of accumulating risk — our physicians read your results against optimal, not just normal.
Why does South Asian physiology need different attention?
South Asians develop cardiovascular disease roughly a decade earlier than Western populations, and insulin resistance appears at lower body weights. Reference data built on Western cohorts under-estimates that risk. Our physicians interpret your markers in that context — it is one of the reasons physician review matters more than a printed report.
Can biological age change?
Some biological-age measures change with training, sleep and diet, though effects in trials so far are modest. No therapy we offer is an anti-ageing treatment. Members track their trend through quarterly retesting, and no outcome is promised in advance — that is what makes this medicine rather than marketing.
Is any of this a diagnosis or treatment recommendation?
No. Everything on this page is educational. Diagnosis and treatment decisions at Genoryx are made only by our physicians, after your assessment, in consultation with you.
What evidence standard do Genoryx protocols follow?
Every protocol is physician-designed and calibrated to your biomarkers. We are conservative by design: interventions with strong evidence are core protocol; promising-but-early science is offered with honest framing; and we will tell you plainly when the evidence does not support something — even if it is fashionable.
Educational content, reviewed by Dr. R. Brahmananda Reddy, MBBS, MSc Dermatology (University of Hertfordshire, UK). Nothing on this page is a diagnosis or treatment recommendation.